Bring the cohort you already have. See what matters. Follow it immediately. DataStoryMD maps the data, brings your field’s knowledge to the first view, and surfaces patterns before you have to formulate the perfect question. As the investigation moves, the definitions, the methods and the safeguards move with it.
A clinician-native research workspace for real-world clinical data.
Coded columns, value legends jammed into headers, sentinels, mixed languages. DataStoryMD maps the columns to clinical meaning before it models anything, and names the ones it could not: on the demo cohort that is 132 of 136.
Named, correctly typed, modeled, and written up in a sentence a clinician can read aloud.
Having an hour free is not the same as having an hour to research. Most of it goes into operating the machinery: preparing the data, specifying variables, choosing a method, briefing a statistician, waiting, then reconstructing where you were. Every new question pays that cost again, and the questions that never feel worth the cost are the ones that quietly go unasked.
Natural-language tools make each request easier to execute, and that is a real gain. It is not the same as making the next question cheap to ask. You still have to formulate it, hold the context yourself, steer the system and check that it understood you. DataStoryMD is built so the next scientifically valid question costs almost nothing to follow, and is held to the same standard as the one you planned.
Most research tools begin after the hard part: once someone has framed the question, chosen the outcome, cleaned the columns and picked the test. This one begins at the file, and lets the thinking go wherever it goes.
Starting this easily usually costs you depth. That is the trade every simple tool makes. Here you get both.
Dozens of related results collapse into a handful of clinical themes, each scored and ready to open. Overview first, detail when you ask for it, so the pattern recognition you already have gets something to act on, instead of a table to grind through.
Counts from the bundled 300-patient simulated cohort. TCGA-OV, with 28 mapped clinical fields, tests 19.
Then keep going: the pathway map, cohort comparison, and live subgroup drill-down are built to be explored, not screenshotted. See them in the live demo →
The interaction model is not a design preference. It follows established results on how people actually investigate data, including two controlled experiments that bear directly on what this product is for.
Adding 500 ms of latency to exploratory analysis measurably reduced how much of the data people covered, how many observations and generalisations they made, and how many hypotheses they formed. Delay does not just annoy. It suppresses discovery.
A visual interactive tool for clinical research produced hypotheses faster, and rated lower on feasibility and quality. Removing friction without keeping the methodology honest buys volume at the cost of worth.
Those two experiments are the argument for this product in one line: speed changes how much you find, and guardrails decide whether it was worth finding. What these results establish is the design; whether this product improves research outcomes is a question we intend to measure, not one we claim answered.
Everything that has to happen for a cohort to become a finding, and which side of the screen it happens on. The machinery takes the preparation, the scanning and the bookkeeping. The judgement never leaves your hands.
Opens the file you already have. Profiles every field, maps local names and codes, resolves units, missingness and repeated measures into clinical concepts, and says plainly what it could not resolve.
Confirm anything consequential. You start from your dataset, not from an analysis-ready statistical specification you had to write about it first.
Builds the overview (variables, outcomes, timelines and cohort structure) before any single model takes over the screen.
Notice what is interesting. Patterns, gaps and distributions, in the context that makes them mean something.
Scans broadly, behind gates: associations, subgroups, survival, thresholds, interactions, trajectories, and only where the design permits the question.
Decide what deserves attention. Whether a result is clinically plausible, and whether it matters, stays a human judgement.
Recomputes without rebuilding. The filter, the focal variable, the outcome and the adjustment set all stay attached to the same analysis.
Test the idea directly. Split it, compare, drill down, change what it adjusts for, challenge the explanation you were given.
Keeps the context. A finding stays linked to its methods, assumptions and evidence instead of becoming a screenshot in a folder.
Turn one observation into the next question, while everything you built to get there is still standing.
Assembles methods, results and figures from the same analytical record you just explored, so the write-up matches what was actually run.
Interpret, edit, conclude. It accelerates the writing. The science, and the authorship, remain yours.
The left column makes statistical decisions and states every one of them: which model, which adjustment set, what it refused and why. What it does not do is decide whether a result is clinically plausible, or what it means, and the second kind is the reason you were the one looking at this cohort in the first place.
Every finding opens. See a pattern, open it, split it, compare it, change the population, follow a pathway, challenge it, inspect the evidence. This is the part you do yourself, and you do it by acting on what you notice rather than by composing an instruction for each move. No request, no queue, no one to ask.
Every control above is in the live demo, and every number is one the engine produced on the bundled 300-patient cohort. The same adjustment sets, multiplicity correction and time-order rules apply whichever way you got here, so a question you followed on impulse is held to the same standard as the one you planned, and is labelled exploratory when it is.
The parts a findings list can't give you.
Most of a session is recognising something and following it. Sometimes a question is quicker said than found, so type it and get a real answer with the statistics behind it. No query language, no pivot tables.
One click to a formatted Word or PowerPoint document, figures, methods, and citations included.
Governed Domain Packs encode how a clinical field is structured: what the variables mean, what matters, how time is ordered, which relationships deserve attention and which analytical safeguards apply. The knowledge changes what the product does, not merely the terminology it displays.
Any tool can surface a correlation. The harder question is which associations reflect biology and which are artifacts of how the data was collected.
On this cohort it set aside 67 outcome candidates as ineligible and excluded hundreds of biased comparisons, each with a stated reason.
Deterministic by design. The same data and the same rules produce the same analysis, from a fixed statistical engine rather than a language model.
Every result is traceable: the estimate, its uncertainty, what it was adjusted for, and the decisions behind it.
More treatment lines means the patient lived long enough to receive them. Survival drives the count, not the reverse.
The vocabulary, the chronology, the endpoints, the confounders and the literature all live in a governed Domain Pack the engine reads, so a specialty is something it can be taught. This is not generic AI with medical vocabulary: the pack changes the research behavior of the system. Depth differs by pack, and we say which is which.
Survival, HRD and BRCA, platinum sensitivity, debulking, and its estimates are reported beside the published TCGA-OV literature.
Trimester uterine- and umbilical-artery Doppler, sFlt-1/PlGF, pre-eclampsia and growth-restriction screening. The engine reads real-world windowed columns automatically. In active clinical validation before it goes public.
Name your field’s concepts, endpoints and timelines once. The same engine then handles the messy data, the adjusted models and the caveats, on your specialty.
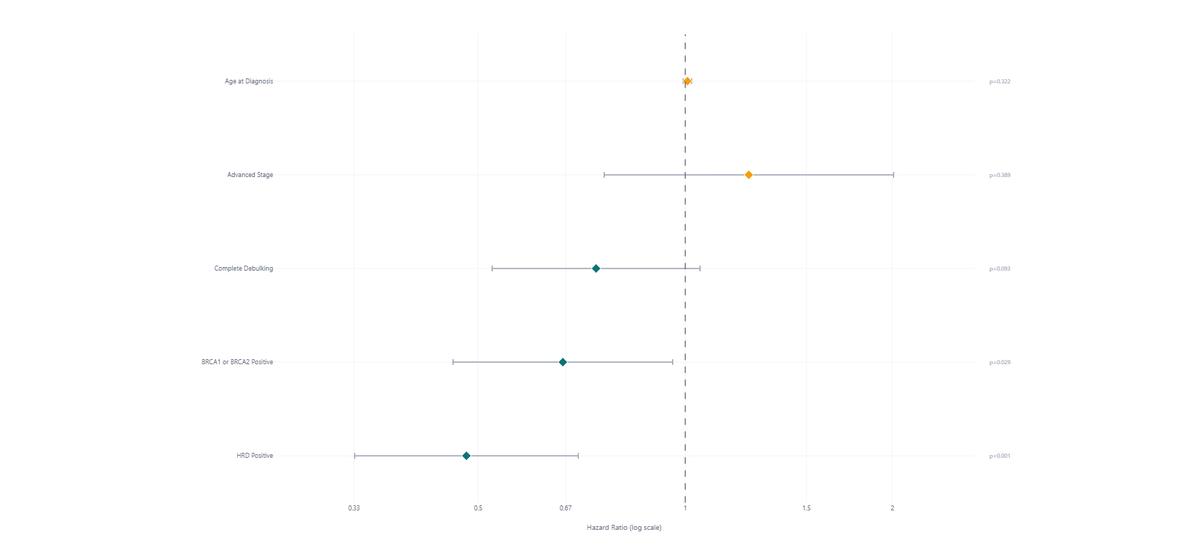
So we ran it on public cohorts whose results are already in the literature, and checked every number we could, against the peer-reviewed paper and the consortium that analysed those exact patients.
Read the full validation report →
What you open is what we checked. The demo carries this exact 316-patient cohort, the same patients Birkbak et al. analysed, and the same file these hazard ratios were computed on. Like for like, no larger-export caveat.
Sources: Hosmer & Lemeshow, Applied Logistic Regression 2nd ed. · Birkbak et al., PLoS One 2013;8(11):e80023 · TCGA Research Network, Nature 2011;474:609–615. Based upon data generated by the TCGA Research Network.
No signup, no upload. Three cohorts are waiting inside: a simulated ovarian cohort with every field populated and the ground truth known, the real TCGA-OV patients the hazard ratios above were computed on, and a simulated obstetric cohort. Pick one and it runs to a full report.
Private beta. Your data never leaves your machine: the tool runs locally and the analysis is offline.
Install, point it at a spreadsheet, and read the findings. Ten minutes end to end.
Clinical intuition, amplified.
Best on a laptop or desktop. The analysis workspace uses wide tables, survival curves and a pathway map, so on a phone this page reads fine, but the tool itself wants a bigger screen.